
Information and harm reduction only, never medical advice. Sourced from the NHS, TALK TO FRANK, the MHRA and peer reviewed research, and written to say plainly where the evidence runs out rather than filling the gap. Always speak to a qualified clinician before changing anything. See our editorial policy.
TRT pricing in the UK is deliberately difficult to compare, and that is not paranoia, it is how the market is structured. Providers quote different things under the same heading, and the number on the pricing page is rarely the number you end up paying.
This page explains what the components actually are so you can compare providers properly. We do not sell TRT, we are not a clinic, and prescription only medicines cannot be advertised to the public in the UK. We are also not printing specific prices, because they change between providers and over time, and a stale figure is worse than no figure. What does not change is the structure, and the structure is what lets you work out whether you are being quoted fairly.
How the cost is structured
Almost every UK provider builds the same model: something upfront to get you diagnosed and started, then something recurring to keep you supplied and monitored.
The upfront part covers an initial consultation and an initial blood panel. The recurring part covers the prescription, the medication itself, and periodic monitoring bloods with a review.
Where providers differ is which of those sit inside the recurring fee and which are billed separately. That single difference is what makes two clinics quoting similar monthly figures cost very different amounts over a year.
The cost on the NHS
Treatment and monitoring are free. In England you pay the standard prescription charge per item, and a prescription prepayment certificate is worth looking at if you are collecting regularly, since it caps the annual cost. Prescriptions are free in Scotland, Wales and Northern Ireland.
Cost is only one difference; NHS vs private TRT compares thresholds, speed and monitoring as well.
The cost of the NHS route is not money, it is time and uncertainty: waiting for tests, waiting for a repeat, then waiting for endocrinology, with the possibility of being turned down at the first step. Six months from first appointment to treatment is not unusual, and it varies enormously by area.
See how to get TRT in the UK for navigating that pathway, including what to do if your GP declines.
The four parts of a private bill
Consultation. The initial appointment, usually remote, and follow ups. Some providers include follow ups in the recurring fee and some charge each one.
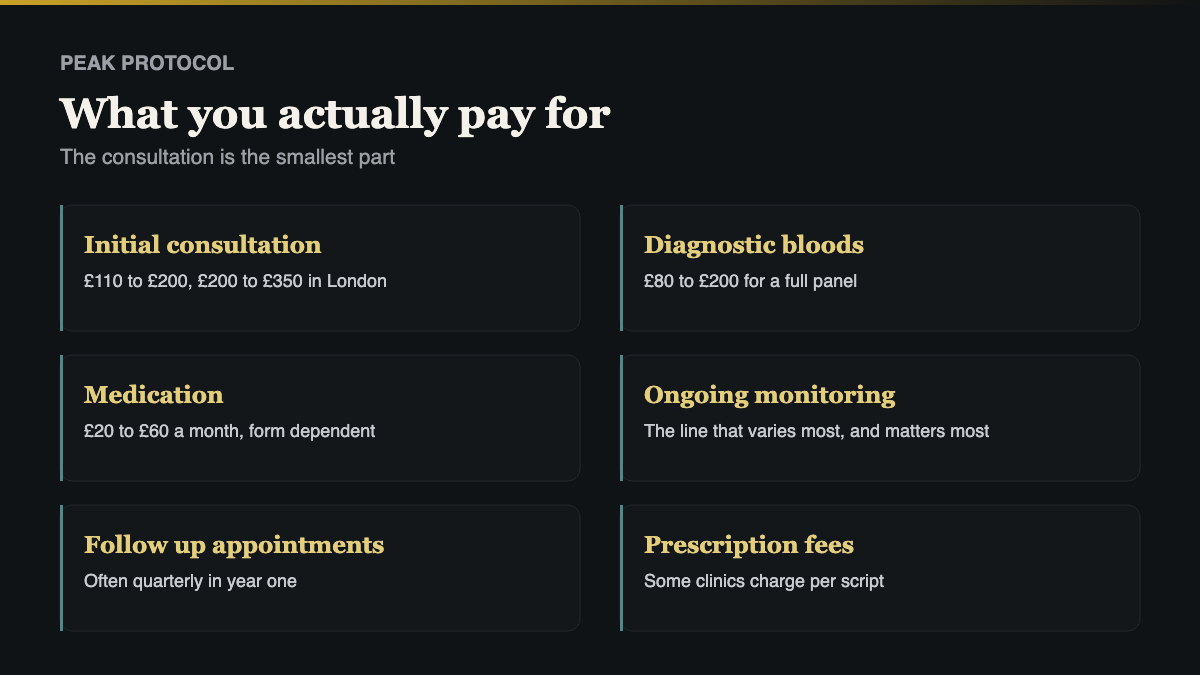
Blood tests. An initial panel, then repeats. This is the component with the widest variation, both in what is measured and how often.
The prescription. The act of a prescriber issuing it, which some providers bill separately from the medication.
The medication. The drug itself, which varies in cost by form more than most people expect.
A provider that bundles all four into one clear monthly figure is easier to compare and usually more honest. One that unbundles them is not necessarily worse, but you have to add them up yourself.
Why headline monthly prices mislead
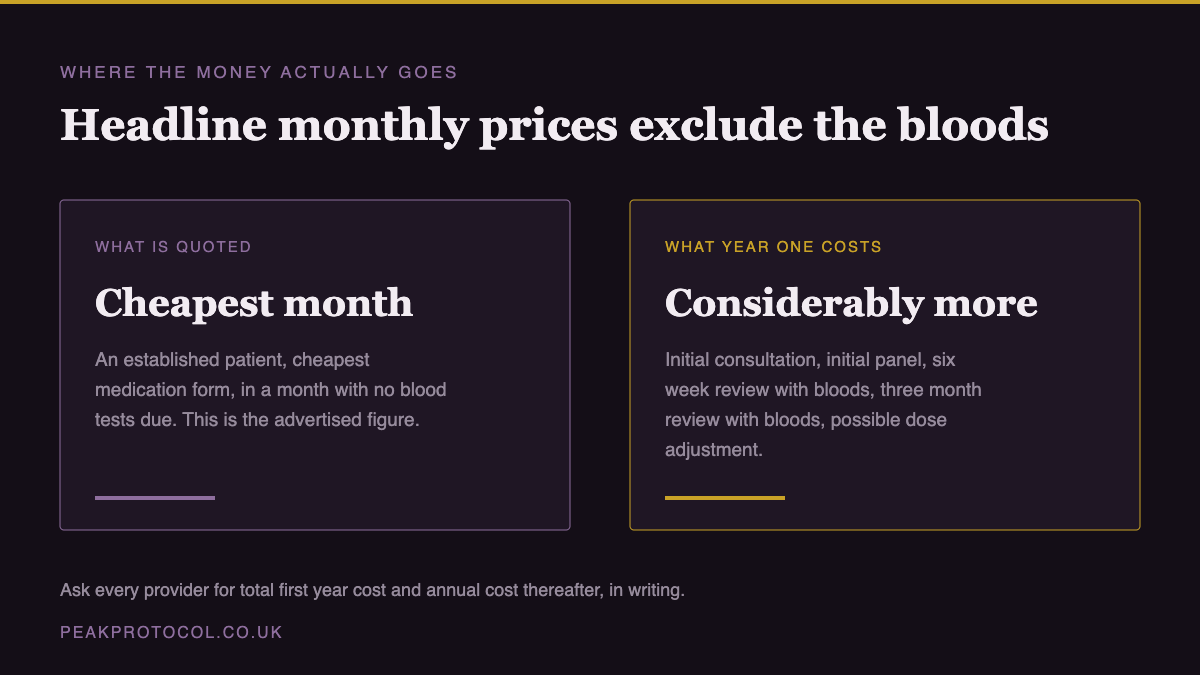
The advertised monthly figure is generally the cheapest possible month: an established patient, on the cheapest medication form, in a month with no bloods due.
Your actual first year contains the initial consultation, the initial panel, a six week review with bloods, a three month review with bloods, and possibly a dose adjustment with another test. Your first year therefore costs substantially more than twelve times the headline figure, and your second year costs considerably less than your first.
Ask for both numbers: total first year, and annual cost thereafter. Any provider unwilling to give you those two figures in writing has told you something useful.
Monitoring: the line item that varies most
Monitoring is where the real difference between providers sits, and it is also the part that matters clinically.
A proper schedule checks testosterone to confirm the dose is doing what it should, haematocrit because testosterone raises red cell production and thick blood carries clot risk, oestradiol, lipids, liver and kidney function, and PSA in older men. Typically at six weeks, three months, then twice yearly.
A cheap provider is frequently cheap because it monitors less. That is not a saving, it is a transfer of risk to you, and the thing being skipped is the specific thing that makes prescribed testosterone different from the unmonitored alternative.
When comparing, ask how many blood panels are included per year and which markers. Two providers can differ by a factor of three on that alone.
Medication, and why the form changes the price
The form you are prescribed affects both cost and convenience, and the cheapest is not automatically the worst.
Shorter acting injections are typically the least expensive and are self administered more frequently, which many people prefer because levels stay steadier. Longer acting injections are given far less often, which suits people who dislike needles, and produce more of a peak and trough. Gels avoid needles entirely and give very stable levels, and they usually cost more and carry a transfer risk to other people through skin contact, which matters around children and partners.
Ask what the clinic prescribes by default and why, and whether alternatives are available at a different price. A provider that only offers one form is limiting your options for their convenience rather than your treatment.
Shared care, the biggest lever on lifetime cost
This changes the lifetime figure more than any difference between clinics, and most people do not ask about it until they are already committed.

Under shared care, a private specialist diagnoses and initiates treatment, then your NHS GP takes over prescribing and monitoring under an agreed protocol. Your ongoing cost drops to prescription charges.
It is entirely discretionary. Your GP is not obliged to accept it, and many practices decline for TRT specifically. Ask your practice before you choose a private provider, because a yes turns a lifelong private cost into a temporary one, and a no means budgeting for private monitoring indefinitely.
Also worth asking prospective clinics whether they will write to your GP proposing shared care. Some do routinely. Some do not, and the ones that do not have an obvious commercial reason.
How to compare clinics fairly
Build a small table before you speak to anyone, with a row for each provider and a column for: total first year cost, annual cost after year one, number of blood panels included, which markers are in the panel, whether follow up consultations are included, which medication forms are offered, whether they support shared care, and CQC registration.
Filling that in takes an hour of emails and it is the single most useful hour you will spend on this. It also flushes out providers who will not answer in writing, which is itself the answer.
Red flags
A prescription before any blood test. The clearest signal of all, and it makes every other consideration irrelevant.
Monitoring sold as an optional extra. Monitoring is the treatment, not an accessory to it.
Long contracts or upfront annual payments before you know the treatment suits you.
Anything else sold alongside, particularly compounds that are not testosterone, or supplements bundled into the fee.
Marketing that leads on physique rather than symptoms. A clinic treating a medical condition talks about fatigue, libido and mood.
More on assessing clinics in our TRT guide.
Six questions to ask before paying
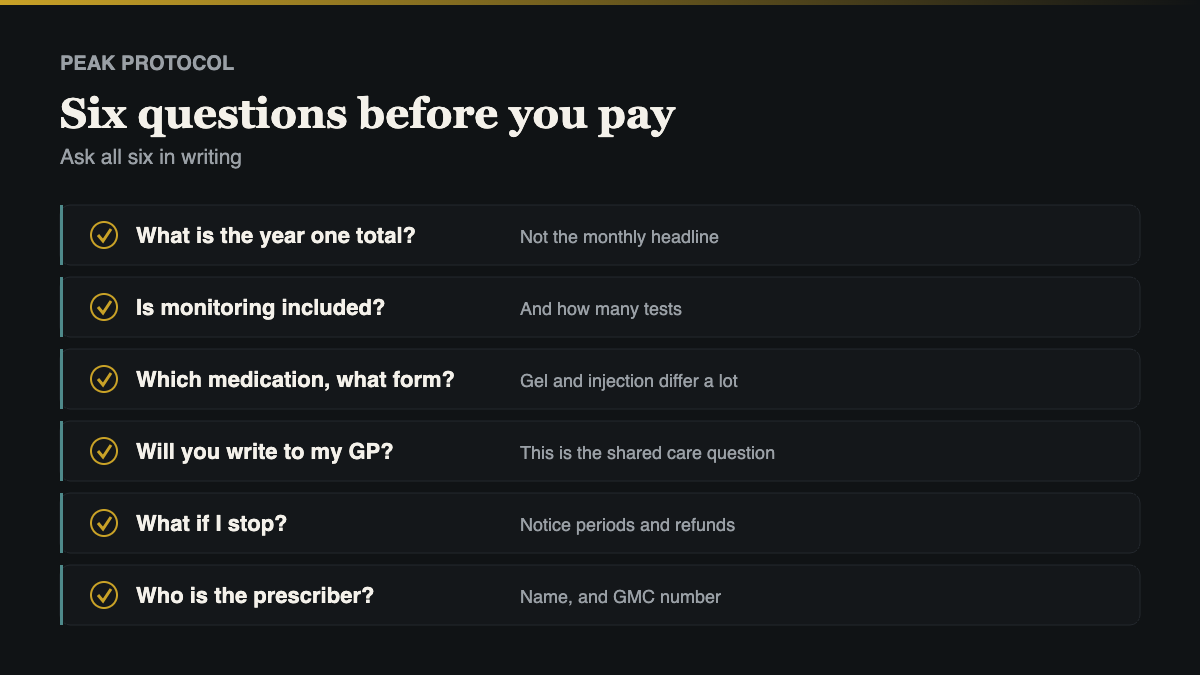
- What is the total cost of my first year, including all bloods and consultations?
- What is the annual cost after that?
- How many blood panels are included per year, and which markers?
- What happens if my results come back normal?
- Will you write to my GP proposing shared care?
- Who is the prescriber, and what is their GMC or GPhC number?
Ask all six by email so you have the answers in writing. The fourth is the one that separates a clinic from a supplier.
Hidden items people forget
Repeat consultations after a dose change. Additional bloods if something needs rechecking. Injecting supplies if not included. Blood pressure monitoring at home, which you should be doing and which costs very little. And the cost of switching provider later, since a new clinic will usually want its own baseline panel rather than accepting someone else’s.
None of those are large individually. Together they are the difference between the quoted figure and the real one.
Switching provider later
People move provider more often than the market admits, usually because monitoring turned out to be thinner than expected or because a shared care request was refused.
Two things make switching cheaper. Keep every blood result with its date, reference ranges and originating laboratory, because a new provider that will accept recent third party bloods saves you a full panel, and some will. And ask before you move whether they accept external results, because the answer varies and it is worth several hundred pounds.
Do not stop treatment while you switch. A gap means levels fall and symptoms return, and you may end up rebuilding a dose you had already settled.
Think in decades, not months
The comparison most people make is between clinics this month. The comparison that matters is over twenty or thirty years, because for most people this is a lifelong treatment.
Over that horizon three things dominate, and the monthly headline is not one of them. Whether you eventually move to NHS shared care. Whether your provider is still operating in ten years, since this is a market with a lot of new entrants. And whether your records are portable, which comes back to keeping your own copies.
A slightly more expensive provider that monitors properly, supports shared care and gives you your data is a better long term decision than the cheapest monthly figure. That is an unusual thing to conclude on a page about cost, and it is the honest one.
Is private treatment worth the money
It depends entirely on your NHS experience, and that is not a dodge.
If your GP tests you promptly, the result is clearly low and the local endocrinology wait is reasonable, the NHS route is free, properly monitored and integrated with the rest of your medical record. There is no advantage to paying.
If you have been declined a test outright, or the wait is many months, private bloods at minimum are worth it to establish the facts, and you can then decide about treatment with actual numbers in hand.
What is never worth it is buying testosterone online instead. It is unmonitored, the seller is committing a supply offence, and it makes the underlying question permanently harder to answer.
Five ways people overpay
Five patterns account for almost all of the money wasted, and every one of them is visible before you pay anything.
One, comparing consultation fees. The consultation is the smallest part of the TRT cost and the only part most clinics advertise. It tells you almost nothing about the year.
Two, ignoring monitoring. Monitoring is not an optional extra on top of treatment, it is the treatment. A service that quotes a low monthly figure and bills separately for every blood test frequently has a higher real TRT cost than one that looks expensive up front.
Three, never asking about shared care. This is the biggest single lever on lifetime TRT cost and most people never raise it. Once you are stable, a GP can take over prescribing while a specialist oversees, which turns a monthly private bill into a prescription charge.
Four, paying for a year in advance. Doses and forms change in the first year, and a prepaid package removes your ability to leave a service that turns out to be poor.
Five, forgetting this is for life. A difference of £40 a month sounds trivial and is nearly £15,000 across thirty years. TRT cost decisions compound in a way that almost no other health purchase does.
Working out your real cost over a year
The only honest way to compare is over twelve months, with everything included. Work it out like this.
Add the year one total. Initial consultation, diagnostic bloods, medication for twelve months, every follow up appointment, and every monitoring blood test. Ask each clinic for that number in writing. The gap between the advertised monthly figure and the real TRT cost is often two to three times.
Then ask what year two looks like. It is usually lower, because the diagnostic work is done and monitoring drops in frequency once you are stable. A clinic that cannot tell you is not thinking about you as a long term patient.
Then ask the shared care question directly. Will you write to my GP proposing shared care once I am stable? A yes changes the lifetime TRT cost by an order of magnitude. A no, or a vague answer, is worth taking seriously as a signal.
And check the NHS route properly first. Prescriptions are free in Scotland, Wales and Northern Ireland and just under £10 an item in England, and the diagnostic standard is higher. How to get TRT in the UK covers the steps, TRT UK covers what treatment involves, and the city pages cover local differences from London to everywhere else. Peak Protocol takes no referral fees from any clinic.
TRT cost and clinics: common questions
How much does TRT cost in the UK?
On the NHS, prescription charges only. Privately, the structure is an initial consultation and panel, then a recurring fee covering prescription, medication and monitoring. Ask each provider for total first year cost and annual cost thereafter, because headline monthly figures exclude the bloods.
Is TRT available on the NHS?
Yes, with symptoms and confirmed low testosterone, though waiting times vary considerably by area.
Why do private TRT clinics vary so much in price?
Mostly monitoring. Cheaper providers frequently include fewer blood panels or fewer markers, which is a transfer of risk rather than a saving.
Can my NHS GP take over my private TRT prescription?
Sometimes, under a shared care agreement. It is discretionary and many practices decline for TRT, so ask your own practice before choosing a provider.
Which form of TRT is cheapest?
Shorter acting injections are typically least expensive, gels usually most. Cost is only one factor, since the forms differ in stability of levels and in transfer risk to other people.
What is the real TRT cost in the UK per year?
Privately, usually £1,000 to £2,400 in year one including diagnosis, medication and monitoring, and somewhat less thereafter. On the NHS it is free in Scotland, Wales and Northern Ireland and just under £10 per prescription item in England.
Why do TRT cost quotes vary so much between clinics?
Because they include different things. Some quote medication only, some include monitoring, some charge per blood test and per prescription. The only fair comparison is a written year one total covering consultation, diagnostics, medication and every monitoring test.
Can I reduce my TRT cost by moving to my GP?
Yes, and this is the biggest available saving. Under a shared care agreement your GP prescribes while a specialist oversees, which replaces a private monthly bill with an NHS prescription charge. Ask any private clinic whether they will write to your GP before you commit.